
The Evolution of Brain Monitoring: from Invasive Drills to Discrete Microimplants
A single baseline number is no longer enough to diagnose complex cerebral pathologies. In May 2026, a research paper published in Science from the American Association for the Advancement of Science applied physics-informed artificial intelligence to magnetic resonance imaging, capturing brain-wide cerebrospinal fluid dynamics in vivo without invasive tracers. This imaging uncovered subtle pulsatile fluid oscillations that correlate with clearing metabolic waste through the glymphatic network.
At the same time, clinical attention has turned toward the blood-brain barrier. As detailed in Wiley & Sons neurovascular research, systemic arterial hypertension triggers microscopic endothelial breakdown long before catastrophic vascular accidents happen. This blood-brain barrier disruption causes localized vasogenic leakage, impairing normal fluid compliance and driving subclinical intracranial hypertension.
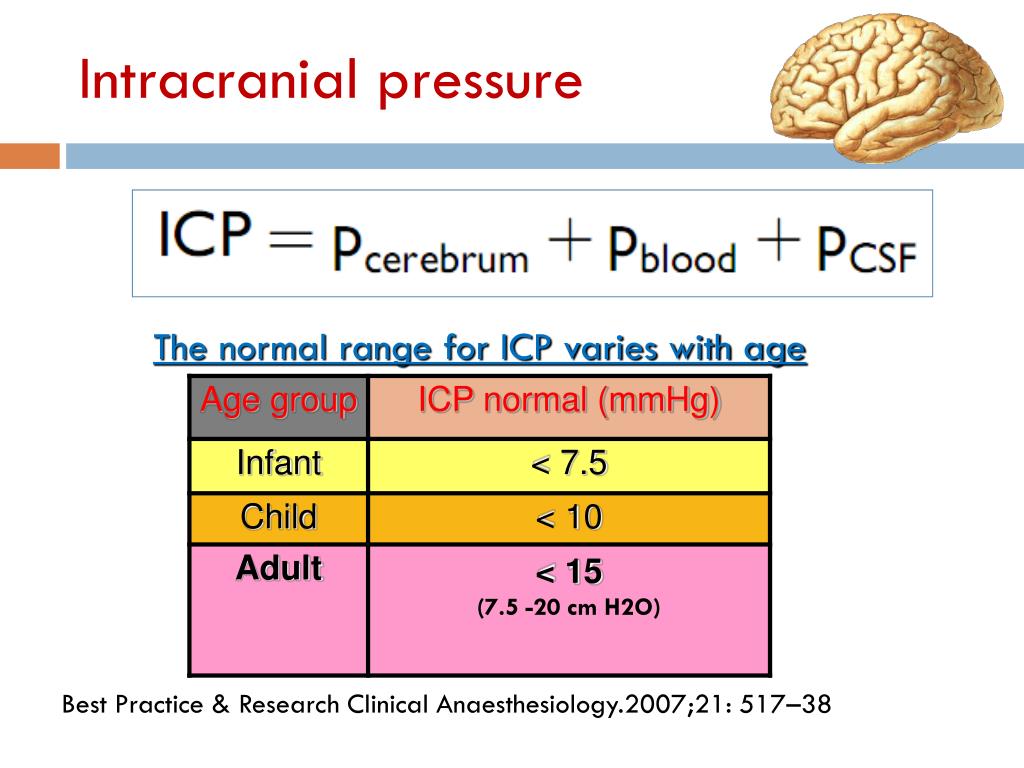
These microvascular shifts help explain conditions like idiopathic normal pressure hydrocephalus, which primarily affects older adults. Patients experience a clinical triad of gait disturbances, urinary incontinence, and cognitive decline, yet standard spinal taps yield pressure readings within the normal 7 to 15 mm Hg range.
A February 2026 study published in Frontiers revealed that while baseline resting pressure looks normal in these patients, their intracranial compliance is badly damaged. The brain loses its elastic cushion. Pulsatile cardiac pressure waves reverberate through stiffened cerebral tissue, transmitting along the peri-optic subarachnoid space directly to the eye. By tracking retinal biomarkers and optic nerve sheath diameters using non-invasive ocular scanners, ophthalmologists and neurologists can catch abnormal fluid stiffness early, protecting patients from permanent nerve injury.





